
Tirzepatide is a prescription peptide medicine that acts on two hormone receptors, GIP and GLP-1. It can lower blood sugar and help eligible patients lose weight, but the product name matters: Mounjaro and Zepbound contain the same active ingredient and have different approved uses. A vial advertised online as a research peptide is not automatically equivalent to either medicine. [1] [2] [6]
Alongside the weight-loss percentage, check who took part, which product they received, what happened over time and which risks occurred.
Related dosage pages: For vial-specific concentration, reconstitution, and measurement examples, see Tirzepatide (5 mg Vial) Dosage Protocol, Tirzepatide (10 mg Vial) Dosage Protocol, Tirzepatide (15 mg Vial) Dosage Protocol, and Tirzepatide (30 mg Vial) Dosage Protocol. Each linked protocol remains a separate reference because vial strength changes concentration and syringe-unit calculations.
What is tirzepatide used for?
| Prescription product | Current U.S. approved uses |
|---|---|
| Mounjaro | Blood-sugar control alongside diet and exercise in adults and children aged 10 or older with type 2 diabetes. Its August 2026 labeling also includes reducing major cardiovascular events in high-risk adults with type 2 diabetes. [1] |
| Zepbound | Long-term weight management in adults with obesity, or overweight with a weight-related condition; also moderate-to-severe obstructive sleep apnea in adults with obesity. These uses accompany reduced-calorie eating and increased activity. [2] |
Approval applies to a particular product, population and use, not a guaranteed result for everyone. It doesn’t make the brands, devices or an unapproved preparation interchangeable without a prescriber’s review.
How tirzepatide works
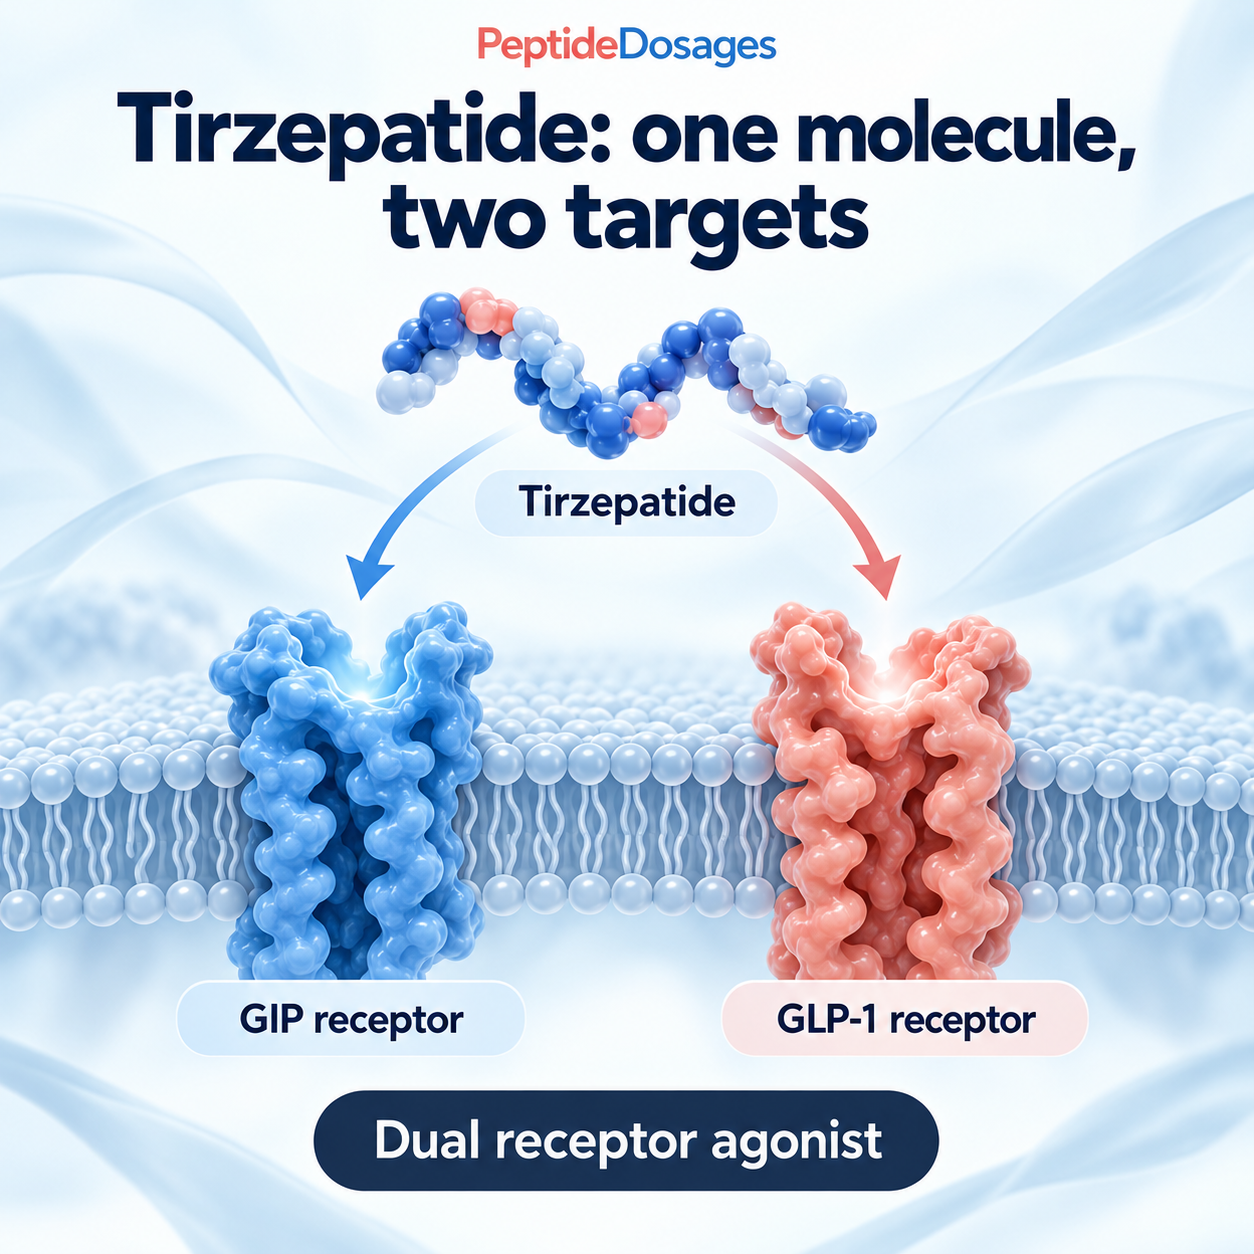
GIP stands for glucose-dependent insulinotropic polypeptide; GLP-1 stands for glucagon-like peptide-1. Tirzepatide activates receptors for both. Its effects include supporting insulin release when glucose is elevated, reducing inappropriate glucagon secretion and slowing stomach emptying. It also affects appetite and food intake. [1] [7]
That is different from a stimulant that simply makes someone feel more energetic. It is also different from semaglutide, which acts at the GLP-1 receptor rather than both GIP and GLP-1 receptors. Receptor count alone does not tell you which medicine will suit a particular person.
How much weight loss did clinical trials show?
The strongest evidence comes from randomized trials, not individual before-and-after photos. In SURMOUNT-1, 2,539 adults with obesity, or overweight plus a related complication, were followed for 72 weeks. People with diabetes were excluded. [3]
| Study group | Average reduction from starting weight |
|---|---|
| Tirzepatide 5 mg weekly | 15.0% |
| Tirzepatide 10 mg weekly | 19.5% |
| Tirzepatide 15 mg weekly | 20.9% |
| Placebo | 3.1% |
These are study-group averages, not starting doses or a personal schedule. The trial included gradual dose escalation, and its estimates included participants regardless of whether they discontinued treatment. Gastrointestinal symptoms were the most common adverse effects, particularly during escalation. [3]
A percentage also depends on starting weight. A 15% reduction is not the same number of pounds for every person. Neither this table nor a dramatic testimonial can reliably tell an individual when they will lose 20 pounds.
Tirzepatide versus semaglutide
SURMOUNT-5 directly compared the medicines in 751 adults with obesity but without type 2 diabetes. At 72 weeks, average weight reduction was 20.2% with tirzepatide and 13.7% with semaglutide. The trial used maximum tolerated weekly doses of 10 or 15 mg for tirzepatide and 1.7 or 2.4 mg for semaglutide. It was randomized but open-label, meaning participants and investigators knew the assigned treatment. [4]
This supports greater average weight loss with tirzepatide under those study conditions. It does not mean milligram doses are equivalent, that everyone should switch, or that the result applies unchanged to people with diabetes. Side effects, medical history, access and the treatment goal still matter.
Quick check: does a higher average mean a better result for everyone?
No. A trial compares groups. An individual may respond differently or be unable to tolerate a treatment. The study population and the actual doses tested matter just as much as the headline percentage. [4]
What happens after treatment stops?
SURMOUNT-4 helps answer that. After an initial 36-week treatment period, 670 participants were randomized either to continue tirzepatide or to switch to placebo for another 52 weeks. The continuing group lost a further 5.5% on average; the placebo group gained 14.0%, measured from their weight at randomization. [5]
That 14% is not “14% of the pounds originally lost.” It is a change relative to body weight when the randomized period began. The findings show why a long-term plan matters. They do not establish that every person must stay on the same treatment indefinitely, or that a particular taper prevents regain.
Does tirzepatide protect the heart?
Mounjaro’s current label includes cardiovascular-risk reduction for high-risk adults with type 2 diabetes. The supporting comparison with dulaglutide established noninferiority for major cardiovascular events, but did not establish superiority. Those are different statistical conclusions. The approval should not be turned into a claim that tirzepatide outperformed dulaglutide on that endpoint or prevents heart disease in anyone using it for weight loss. [1]
Side effects and important precautions
Common tirzepatide side effects include nausea, diarrhea, vomiting, constipation and stomach discomfort. Report symptoms that are severe, persistent or interfere with eating and drinking. Persistent severe abdominal pain, particularly with vomiting or pain extending toward the back, needs prompt medical assessment. Trouble breathing or swelling of the face or throat warrants emergency care. [7]
The boxed warning concerns thyroid C-cell tumors seen in rats; whether this happens in humans is unknown. A personal or family history of medullary thyroid carcinoma, or MEN2, is a contraindication. [1]
Other important concerns include pancreatitis, gallbladder disease, dehydration-related kidney injury and severe gastrointestinal reactions. Zepbound is not recommended with severe gastroparesis. Low blood sugar is more likely when combined with insulin or certain diabetes medicines. Tell the anesthesia team about treatment before a procedure because delayed stomach emptying can affect aspiration risk. [2]
For oral hormonal contraception, the Zepbound label advises a non-oral method or added barrier protection for four weeks after starting and for four weeks after each dose increase. Pregnancy or plans for pregnancy need a prescriber’s review. [2]
Prescription medicine, compounded tirzepatide and research vials
These are not three names for the same regulated product. FDA-approved tirzepatide comes as a liquid medicine in specified pens or vials. A freeze-dried research vial requiring mixing is not one of those approved presentations. [2] [7]
Compounded medicines are not FDA-approved and do not undergo the same premarket review for safety, effectiveness and quality. FDA has reported concerns about measurement errors and dosing beyond approved labeling, and warns against unapproved products sold to consumers under research-only claims. Obtain prescribed treatment through a licensed pharmacy and have unclear instructions checked by the prescriber or pharmacist. [6]
A number marked on a syringe is not enough to identify a drug dose. It depends on the actual concentration and product. Do not copy “units” from someone else’s vial or use a research calculation to reinterpret a prescription device.
Questions worth bringing to an appointment
- Which approved use applies to my situation, and what outcome are we monitoring?
- How will my other medicines and relevant medical history affect the choice?
- What symptoms should prompt a call, and how will follow-up work?
- What is the plan if the medicine is ineffective, poorly tolerated or no longer accessible?
Bottom line: Tirzepatide has substantial clinical evidence, but the evidence belongs to defined treatments and populations. A realistic discussion includes benefits, adverse effects, product quality and long-term follow-up, not just a weight-loss percentage. This overview cannot determine whether it is appropriate for you.
Related dosage protocols and research
Explore related research, dosage references and guides below. Vial strengths have separate references because concentration and syringe-unit calculations differ. A comparison does not mean the compounds are interchangeable.
Matching dosage protocols
- Tirzepatide (5 mg Vial) Dosage Protocol
- Tirzepatide (10 mg Vial) Dosage Protocol
- Tirzepatide (15 mg Vial) Dosage Protocol
- Tirzepatide (20 mg Vial) Dosage Protocol
- Tirzepatide (30 mg Vial) Dosage Protocol
- Tirzepatide (40 mg Vial) Dosage Protocol
- Tirzepatide (50 mg Vial) Dosage Protocol
- Tirzepatide (60 mg Vial) Dosage Protocol
- Tirzepatide (80 mg Vial) Dosage Protocol
- Tirzepatide (90 mg Vial) Dosage Protocol
- Tirzepatide (100 mg Vial) Dosage Protocol
Further research context
References
- Mounjaro prescribing information. DailyMed. Current label checked October 6, 2026.
- Zepbound prescribing information. DailyMed. Current label checked October 6, 2026.
- Jastreboff AM, et al. Tirzepatide once weekly for the treatment of obesity. N Engl J Med. 2022. SURMOUNT-1.
- Aronne LJ, et al. Tirzepatide as compared with semaglutide for the treatment of obesity. N Engl J Med. 2025. SURMOUNT-5.
- Aronne LJ, et al. Continued treatment with tirzepatide for maintenance of weight reduction in adults with obesity. JAMA. 2024. SURMOUNT-4.
- FDA. Concerns with unapproved GLP-1 drugs used for weight loss. Checked October 6, 2026.
- MedlinePlus. Tirzepatide injection: patient drug information.