

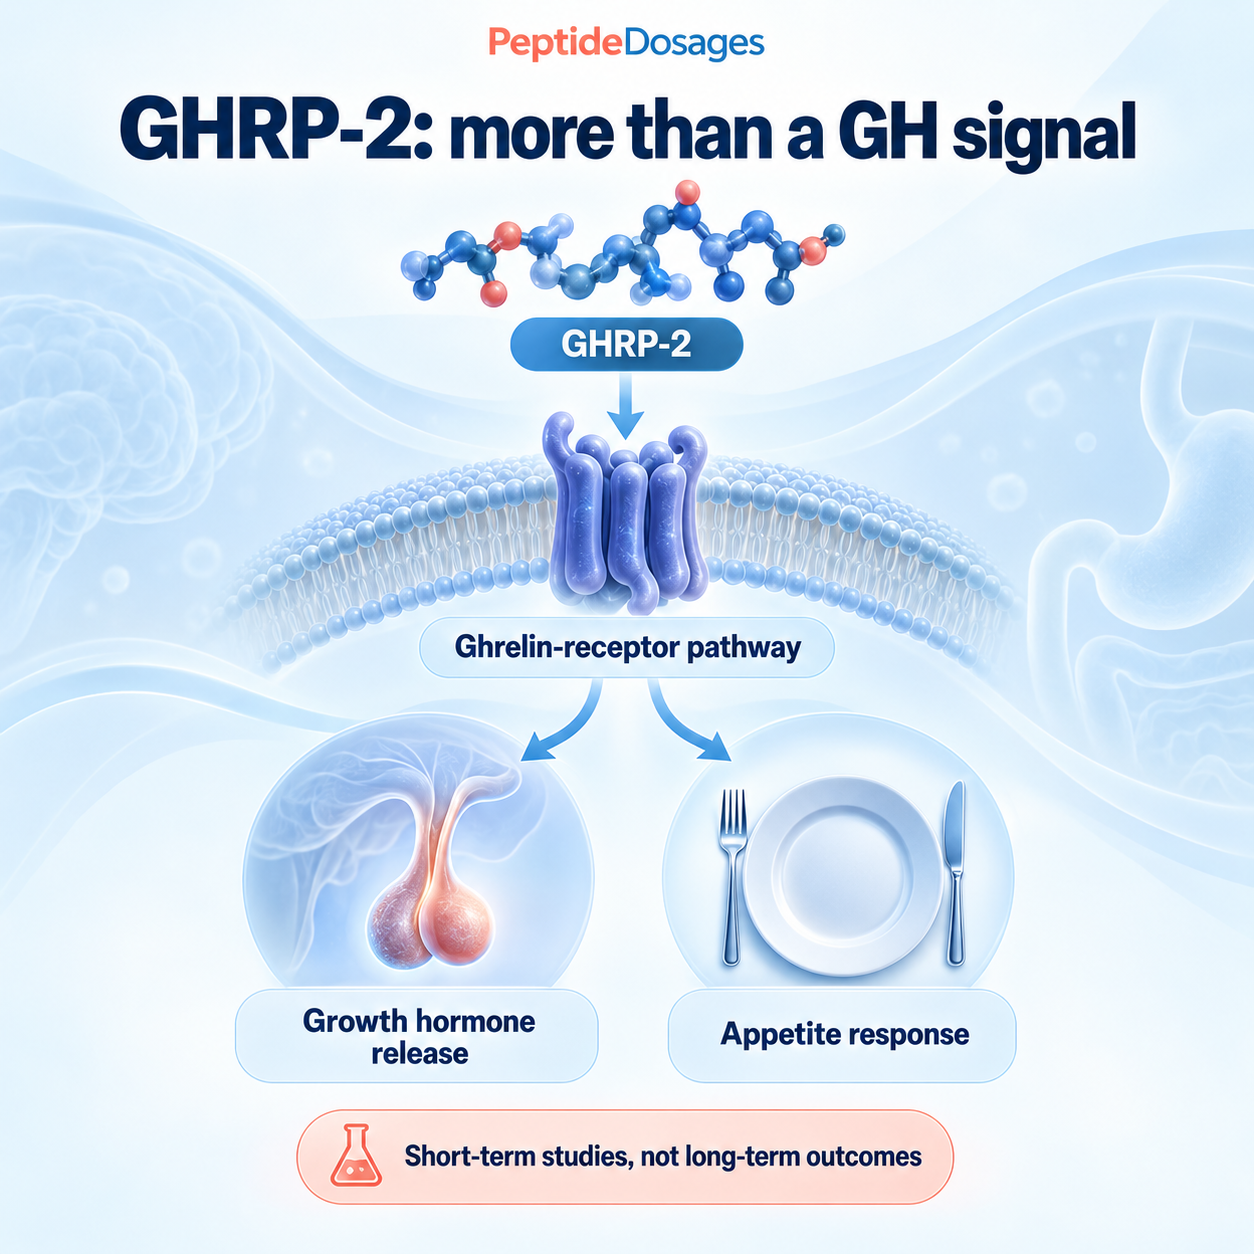
GHRP-2 is a synthetic peptide that stimulates growth hormone release and can increase appetite. Its name stands for growth hormone-releasing peptide-2; it is also called pralmorelin. It activates the ghrelin receptor rather than supplying growth hormone directly. Small human studies demonstrate these short-term effects, but they do not establish the muscle-building, fat-loss or anti-aging results often attached to the name. [1][2]
Who was studied, what was measured and for how long? A hormone rise over a few hours isn’t evidence of better health over several years.
How does GHRP-2 work?
GHRP-2 acts at the growth hormone secretagogue receptor, commonly called the ghrelin receptor. Ghrelin is a natural signal involved in hunger and growth hormone secretion. GHRP-2 mimics some of that signaling and can prompt GH release from the pituitary. That’s why appetite appears alongside hormone release in its research. [1]
It is not HGH in a smaller vial. HGH is the hormone itself; a secretagogue stimulates hormone release. Nor does “stimulating your own GH” automatically make a product safe. A biological signal can have several effects, and the size of a laboratory response is not a safety test.
What do the human studies actually show?
| Study | Finding and limits |
|---|---|
| 7 healthy men, 2005 | During an acute infusion experiment, participants ate about 36% more at a test meal with GHRP-2 than with saline. GH secretion also rose. [1] Limit: One supervised meal does not show long-term weight gain, fat loss or muscle growth. |
| 19 lean or obese adults, 2006 | A randomized crossover study found increased food intake at both tested exposure levels, with a larger response at the higher level. [2] Limit: It tested acute appetite and hormone responses, not a weight-management program. |
| 9 healthy young men, 1998 | Over five days, repeated administration produced a smaller GH response over time and did not increase mean IGF-1. [3] Limit: This small, short study cannot settle every longer-term question. It does show why a first-dose GH peak cannot be assumed to persist. |
These are meaningful findings. They establish that GHRP-2 is biologically active in humans. They are not interchangeable with evidence that a person becomes stronger, loses abdominal fat, sleeps better or lives longer.
Does GHRP-2 make you hungry?
It can. Increased food intake is one of its clearest directly measured effects in the human studies above. The response was seen in lean participants and in participants with obesity. That does not mean everyone will feel the same degree of hunger, or that appetite stimulation is appropriate for someone who wants to gain weight. [1][2]
What about fat loss and muscle growth?
The appetite experiments cannot answer those questions. They did not test months of changes in body composition, training performance or recovery. Likewise, an increase in GH does not prove a sustained increase in insulin-like growth factor-1, or IGF-1. The five-day study is a useful counterexample to that assumption. [3]
If a claim cites a paper, check the outcome rather than the title alone. “GH increased” and “muscle strength improved” are different statements. A believable explanation of a mechanism is the beginning of a research question, not the answer.
Quick check: does a larger GH peak prove better results?
No. It proves a hormone response under the conditions tested. To claim a practical benefit, researchers need to measure that benefit directly, compare it with an appropriate control and monitor harms for a relevant period.
GHRP-2 side effects and safety concerns
Reliable long-term safety estimates for unsupervised wellness use are not established by these small trials. Descriptions such as “minimal side effects” go beyond what they can tell us.
The FDA identifies potential safety risks with compounded GHRP-2 for injectable and nasal use, including immune reactions related to aggregation or peptide impurities. It also notes reports of increased insulin requirements, infection, pancreatitis and deaths among critically ill study participants. The FDA says causality has not been established. Those reports should neither be presented as proof that GHRP-2 caused every event nor dismissed as evidence of safety. [4]
A research label does not resolve these concerns. A purity percentage also does not, by itself, establish sterility, correct identity, suitability for a particular route or clinical safety. People with symptoms they attribute to low GH need medical evaluation, not a peptide trial based on symptoms alone.
Is GHRP-2 approved anywhere?
Japan approved pralmorelin hydrochloride as a diagnostic agent for testing growth hormone secretion. The PMDA records the approval of GHRP Kaken 100 in 2004. [5] A supervised diagnostic test is a narrow use. It does not authorize an online product as a daily treatment for recovery, aging or body composition.
In the United States, the FDA’s significant-safety-risk listing is important context for compounded GHRP-2. Do not interpret the availability of a compounded or research product as FDA approval of its safety and effectiveness. [4]
For athletes, the rules are explicit: the 2026 WADA Prohibited List names GHRP-2, also called pralmorelin, under growth hormone-releasing factors prohibited at all times. [6]
GHRP-2, GHRP-6, ipamorelin and HGH
These names often appear together, but a comparison needs a specific purpose. A mechanism comparison is not the same as a clinical recommendation.
| Compound or group | Useful distinction |
|---|---|
| GHRP-2 | A GH secretagogue with direct human evidence of short-term appetite stimulation. That does not establish a preferred body-composition treatment. [1] |
| GHRP-6 and ipamorelin | Other GH-releasing agents, not interchangeable formulations. The FDA lists safety concerns for these substances too. A claim of a “cleaner” option requires evidence for the exact use being proposed. [4] |
| HGH / somatropin | Growth hormone itself rather than a signal to release it. Read the separate HGH 191AA overview for the distinction between a molecule name and a specific medicine. |
Combining secretagogues does not remove the need for controlled evidence. A larger response from a combination cannot, on its own, establish better outcomes or a safe long-term schedule.
A few practical questions
Is there an established GHRP-2 dose for healthy adults?
The studies discussed here do not establish a general-purpose dose or cycle for healthy adults. Research exposures, a diagnostic test and a bodybuilding schedule are different things. Concentration calculations cannot fill that evidence gap.
Do oral studies prove that a GHRP-2 supplement works?
No. An oral study followed ten children with growth hormone deficiency, a very different population from healthy adults buying a supplement. Its findings cannot establish the effectiveness of an unrelated commercial formulation. Route, formulation and population all matter. [7]
How quickly should someone expect results?
There is no supported universal timeline for muscle, recovery or fat-loss results. Acute hormone and appetite effects are not a countdown to a proven long-term benefit.
Bottom line: GHRP-2 has real human pharmacology, particularly GH release and appetite stimulation. The evidence is much narrower than the wellness claims. Discuss persistent fatigue, appetite changes or suspected hormone problems with a qualified healthcare professional.
References
- Laferrère et al. GHRP-2, like ghrelin, increases food intake in healthy men. 2005.
- Laferrère et al. Obese subjects respond to the stimulatory effect of GHRP-2 on food intake. 2006.
- Nijland et al. Five-day GHRP-2 treatment, response attenuation and IGF-1 secretion in healthy young men. 1998.
- U.S. FDA. Bulk drug substances that may present significant safety risks.
- Japan PMDA. Approved new drugs, including the 2004 pralmorelin diagnostic approval.
- WADA. 2026 Prohibited List, section S2.
- Oral GHRP-2 research in growth hormone-deficient children. 2003.
Related dosage protocols and research
Explore related research, dosage references and guides below. Vial strengths have separate references because concentration and syringe-unit calculations differ. A comparison does not mean the compounds are interchangeable.
Matching dosage protocols
Related protocols and comparisons
Further research context